

Joy Maria Mitchell: Prenatal Cytogenetics – Karyotype, FISH and Clinical Evaluation
Joy Maria Mitchell, Clinical Scientist, Molecular Genetics and Cytogenetics – Medical City Technologist and Quality Control Officer at Hamad Medical Corporation, shared on LinkedIn:
“Prenatal Cytogenetics:
Karyotype + FISH + Clinical Evaluation
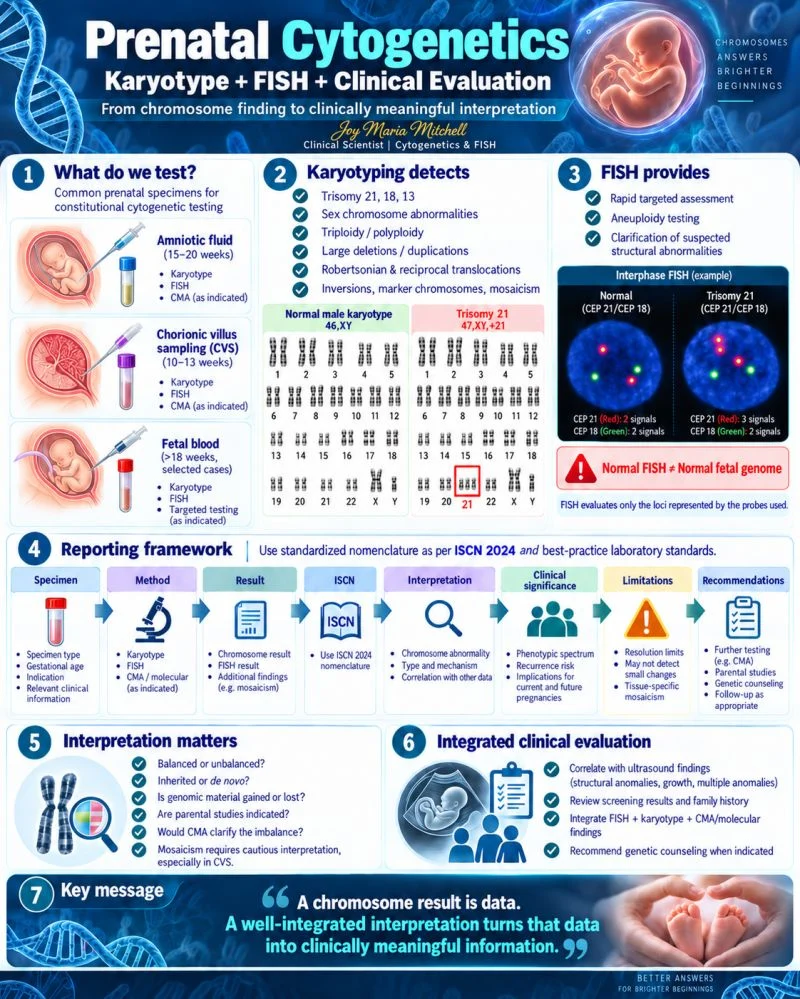
Prenatal Cytogenetics is not simply about identifying 46 chromosomes or reporting FISH as ‘normal’ or ‘abnormal.’ The real value is translating a chromosome finding into a clinically meaningful interpretation for the pregnancy and family.
What do we test?
Common specimens include amniotic fluid, CVS, fetal blood and POC in selected cases.
Karyotyping provides a genome-wide chromosome-level assessment and can detect:
- Trisomy 21, 18 and 13
- Sex chromosome abnormalities
- Triploidy/polyploidy
- Large deletions/duplications
- Robertsonian/reciprocal translocations
- Inversions, marker chromosomes and mosaicism within assay limits.
FISH provides rapid, targeted assessment of specific chromosomes or loci and is useful for aneuploidy testing or clarification of suspected structural abnormalities.
Normal FISH ≠ Normal fetal genome.
FISH evaluates only the chromosomes or loci represented by the probes used.
A strong prenatal Cytogenetics report should communicate:
Specimen – Method – Result – ISCN – Interpretation – Clinical Significance – Limitations – Recommendations.
Standards and Accreditation:They support to ensure the universality and quality. ISCN 2024 | CAP | CLSI | ACMG | ISO 15189 | PT/EQA
These support standardized nomenclature, validated methods, QC, competency, proficiency testing, interpretation and documented limitations.
Interpretation is where the Clinical Scientist adds value.
A result such as 47,XX,+21 should not stop at the ISCN line. The report should explain that the finding is consistent with trisomy 21, its clinical relevance, and recommend genetic counseling and clinical correlation.
Structural abnormalities require deeper assessment:
- Balanced or unbalanced?
- Inherited or de novo?
- Is genomic material gained or lost?
- Are parental studies indicated?
- Would chromosomal microarray clarify the imbalance?
Mosaicism requires caution, especially in CVS. Interpretation should consider specimen type, cells/colonies analyzed, culture findings, ultrasound findings, and possible confined placental mosaicism.
FISH, karyotype, and microarray are complementary—not interchangeable.
- FISH = rapid and targeted
- Karyotype = genome-wide chromosome-level assessment
- CMA = higher-resolution copy-number assessment
Final interpretation should integrate:
Ultrasound + screening results + family history + FISH + karyotype + CMA/molecular findings (indicative).
The key questions are:
- What was found?
- What does it mean?
- How certain is it?
- What are the limitations?
- What additional testing could clarify the finding?
A chromosome result is data.
A well-integrated interpretation turns that data into clinically meaningful information.”
Stay informed with the latest updates in fertility and reproductive medicine on Fertility News.
-
Oct 14, 2026, 17:21Abhijit Kulkarni: The Missing Answer to Repeated IVF Failure May Lie in the Genes
-
Oct 14, 2026, 17:17A Very Special Visit That Made Our Day – Complete Fertility
-
Oct 14, 2026, 17:12Ensuring That Every Woman Receives the Highest Quality of Care Globally – FIGO
-
Oct 14, 2026, 17:08Sukhbir Singh: Why Are Canadians Leaving the Country for Endometriosis Care?
-
Oct 14, 2026, 17:03Angeline Beltsos: Thrilled to Announce That I’m Returning to Patient Care at Vios 2.0
-
Oct 14, 2026, 16:58Juan A. García Velasco: IVI RMA Global Evolves into IVI Institute, Strengthening Research and Innovation in Fertility Care
-
Oct 14, 2026, 16:49Devyanshi Dixit: Acknowledgement Matters After Baby Loss…
-
Oct 14, 2026, 16:28Svitlana Yashchenok: Would You Introduce Non-Invasive PGT-A into Your Fertility Clinic Today?
-
Oct 14, 2026, 16:17Jen Atkinson: Vine Reproductive Is Officially Open in Tulsa