

Ivan Dozzani։ Semaglutide and Pregnancy
Ivan Dozzani, Member of the Board of Directors at the Italian Obesity Society, Umbria, shared a post on LinkedIn about a paper by Robert Matson et al.:
“Semaglutide and Pregnancy: Reassurance Is Not the Same as Safety.
What new real-world evidence tells us about inadvertent first-trimester exposure and what it cannot tell us.
As GLP-1 receptor agonists become increasingly used by women of reproductive age, pregnancy planning and inadvertent exposure are emerging as important clinical challenges.
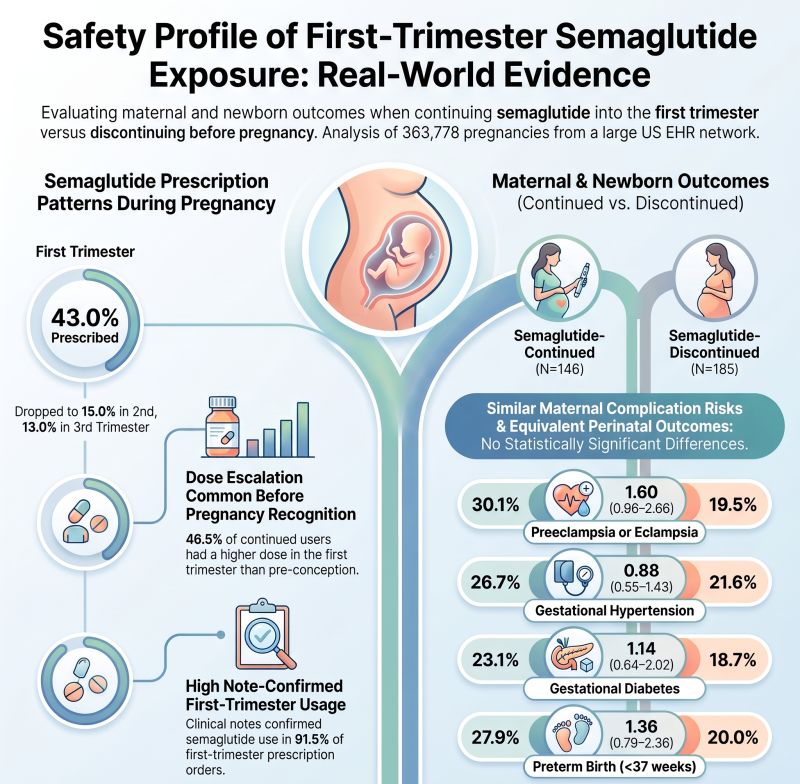
A large US retrospective cohort study analysed 572 semaglutide-exposed pregnancies, including 246 with first-trimester prescriptions.
Three findings deserve attention:
No significant increase in the maternal and neonatal outcomes assessed was detected when semaglutide continuation was compared with discontinuation, after adjustment for confounders and multiple testing.
Absence of statistical significance is not proof of safety. The relatively small number of deliveries and wide confidence intervals mean clinically relevant risks cannot be excluded. Major congenital malformations could not be directly assessed.
A potential safety signal remains. In a secondary comparison with metformin, semaglutide exposure was associated with higher rates of gestational hypertension and gallbladder disease in specific subgroups. These findings require confirmation.
The clinical implication is clear: inadvertent early exposure should prompt individualised assessment, not automatic assumptions of harm but these data do not justify semaglutide use during pregnancy.
For clinicians, the priority extends beyond what to do after conception: contraception, pregnancy intentions and preconception discontinuation must be addressed before prescribing. Current recommendations advise stopping semaglutide at least two months before a planned pregnancy.
The next step is stronger evidence: larger prospective studies with linked neonatal outcomes are needed to assess congenital malformations and define risks more precisely.
In obesity medicine, responsible prescribing means integrating therapeutic benefit, reproductive planning and uncertainty not interpreting reassuring observational findings as a declaration of safety.
Thanks to the authors for contributing evidence to this important and evolving field. Their findings help inform clinical conversations, while reinforcing the need for larger studies with robust maternal and neonatal follow-up.”
Title: Continuing Semaglutide into the First Trimester of Pregnancy Is Not Associated with Maternal or Newborn Complications in Routine Care
Authors: Robert Matson, AJ Venkatakrishnan, Gowtham Varma, Venky Soundararajan
You can read the Full Article.

Stay informed with the latest updates in fertility and reproductive medicine on Fertility News.
-
Oct 31, 2026, 17:52Khalil Faaed: Beyond ROS – The Antioxidant Revolution in IVF
-
Oct 31, 2026, 17:46Tracey Bambrough: World Fertility Day – One World, One in 6, One Conversation
-
Oct 31, 2026, 17:29Emad Sedeek: Embryo Transfer – ESHRE IVF Laboratory Guidelines 2026 Updates, Part 3
-
Oct 31, 2026, 17:22Brian A. Levine: Hip-Hop and IVF Are the Same Age
-
Oct 31, 2026, 17:16Alison Campbell: Excited to Announce the EFRE-ALPHA Embryology Masterclass Webinar No. 3
-
Oct 31, 2026, 17:09Khaled Abu Ali: Building the IVF Unit at American Hospital Dubai
-
Oct 31, 2026, 17:05Hosting a Genetics and Fertility Educational Dinner for Local GPs – Monash IVF Group
-
Oct 31, 2026, 17:01Ahmed Gibreel: IVF After 45 – What Does The Evidence Actually Tell Us?
-
Oct 31, 2026, 16:49Emily Kostina: How and Why Does the Placenta Develop, and What It Does During Pregnancy?